
Clickable Contents
- Disclaimers
- How the Seraph 100 works
- Indications for use
- Frequency of treatments
- Length of treatment
- Heparinization during treatment
- Benefits of treatment (FDA)
- Risks of treatment (FDA)
- FDA approved device settings
- Machine setup for running the Seraph
- Who to treat when resources are limited
- Downloads
This document was created Dec. 7, 2020 for the purpose of bringing a consistent approach to using the Seraph filter for Covid 19 in Meridian, Mississippi. At the time the author, John C. (Jack) Andy, had never treated any patients with the Seraph.
The views expressed in this presentation are those of the author and do not reflect the official policy of the Department of Army/Navy/Air Force, Department of Defense, or U.S. Government.
The Seraph is thought to impart its benefits by removing the pathogen (the bacteria/virus) from the bloodstream. There is good in vitro evidence of this. For me this 8 minute video case report is very suggestive that the filter indeed can have a significant clinical effect in a patient with bacteremia who has Covid 19.
Dr. Stephen Olson, Asst. Chief of Nephrology, Walter Reed Medical Center, on inflamatory markers in Covid 19The Seraph may have some effect on inflammatory markers and cytokines. However my review of the information and in speaking with some of the involved physicians there does not seem to be a consistent effect here. I do not think the presence, absence, decrease or increase in serum cytokines or inflammatory markers should play too much of a role in whether to treat or re-treat a Covid infected patient with the Seraph.
FDA indications for Seraph use
“For the purposes of this EUA, a patient with confirmed COVID-19 infection who is admitted to the ICU with confirmed or imminent respiratory failure is a patient 18 years of age or older who has any one of the following conditions”:
- Early acute lung injury (ALI)/early acute respiratory distress syndrome (ARDS); or
- Severe disease, defined as:
- dyspnea,
- respiratory frequency ≥ 30/min,
- blood oxygen saturation ≤ 93%,
- partial pressure of arterial oxygen to fraction of inspired oxygen ratio < 300, and/or
- lung infiltrates > 50% within 24 to 48 hours; or
- Life-threatening disease, defined as:
- respiratory failure,
- septic shock, and/or
- multiple organ dysfunction or failure.
ExThera Medical (maker of the Seraph) indications for use
“Seraph 100 is indicated for patients with laboratory confirmed and symptomatic COVID-19 with any of the following”: (same as EUA indications above)
- Early acute lung injury (ALI)/early acute respiratory distress syndrome (ARDS);
- Severe disease, defined as:
- dyspnea,
- respiratory frequency ≥ 30/min,
- blood oxygen saturation ≤ 93%,
- partial pressure of arterial oxygen to fraction of inspired oxygen ratio < 300, and/or
- lung infiltrates > 50% within 24 to 48 hours;
- Life-threatening disease, defined as:
- respiratory failure,
- septic shock, and/or
- multiple organ dysfunction or failure.
ExThera Medical Contraindications to Seraph use:
- Patients with proven heparin-induced thrombocytopenia (HIT), or patients with hypersensitivity to heparin
- Patients with low platelet count (<30,000/microliter)
- Known allergy to any device component
- Column Body and End Caps – Copolyester, DuraStar™ Polymer
- End Plate – Hydrophilic porous polyethylene
- Adsorption media, beads – Ultra-high molecular weight polyethylene
- End Point Attached Heparin – Heparin Sodium, USP
- Patients <18 years of age
- Inability to tolerate anticoagulation
- Untreated hypercoagulability
- Treatment deemed clinically futile
- Patient is pregnant
- Known allergy to ethylene oxide (Seraph 100 is sterilized with ethylene oxide)
Hattiesburg Clinic suggested indications for Seraph use
All of the following must be present:
- COVID-19 positive test within 7 days, and
- Hypoxemia requiring FiO2 of 80% or P/F Ratio <150, and
- Receiving other specific treatment(s) for COVID-19 (i.e. steroids, remdesivir, convalescent plasma, etc.)
Hattiesburg Clinic Exclusions for Seraph use:
Presence of a terminal illness/disease, i.e. metastatic cancer, end-stage liver, heart, or lung disease, etc.
An actively viremic pt presenting with or exhibiting a rapid deterioration to serious morbidity.
Dr. Olson on when to use the Seraph filter for Covid 19Dr. Olson on outcomes with earlier vs later treatment
Unfortunately there is no readily available test for Covid viremia and because the Seraph seems to work by removing the virus I believe the key to successful results lie in identifying patients who are actively viremic. With this in mind the aforementioned “actively viremic” pt would demonstrate some combination of the following characteristics:
- Rapidly worsening morbidities involving
- Fever
- Hypotension
- High requirement for supplemental oxygen
- More recent positive Covid test versus less recent
- Dr. Olson on timing of peak viremia
- more recently infected is more likely viremic than less recent (in my opinion this is the most important factor in treatment success by far)
- Caveats:
- A pt. who has been holding his own for a week or two but then takes a rather dramatic turn for the worse could be experiencing a surge in viremia and may benefit significantly from the Seraph
- A pt. who may be a week or two out from his diagnosis but becomes clinically worse related to blood culture confirmed bacteremia may benefit from the bacterial removing properties of the Seraph.
- This is in contradistinction to a pt. who has been doing poorly for a week or more on antibiotics who is culture negative and may be suffering from SIRS (systemic inflammatory response syndrome) or just the culmination of prolonged illness and MSOF (multi-system organ failure).
- Caveats:
- Dr. Olson on timing of peak viremia
- Younger rather than older (if resources are limited)
- Dr. Olson on younger vs. older
- All things being equal a younger pt doing poorly as opposed to an older pt doing poorly is more likely to be severely viremic (although one could make the argument that it takes less viremia to make an older pt do poorly so it would be equally beneficial in both situations).
- Dr. Olson on younger vs. older
- Less comorbidities than more (if resources are limited)
- all things being equal a pt with less comorbidities doing poorly is more likely to be severely viremic than a pt doing poorly with more comorbidities (although one could make the argument it takes less viremia to make a more comorbid pt sick hence both patients would benefit equally from the treatment).
- More ill than less ill to a degree
- because Seraph treatment is more invasive/risky (HD catheter placement/extracorporeal therapy) versus some other forms of therapy its use in patients who are holding their own against the virus may do well to forgo/postpone its use.
- Caveat: A dialysis patient may have a lower threshold for receiving the Seraph as the risks of treatment are inherent i.e. they already have dialysis access and undergo extracorporeal treatments.
- because Seraph treatment is more invasive/risky (HD catheter placement/extracorporeal therapy) versus some other forms of therapy its use in patients who are holding their own against the virus may do well to forgo/postpone its use.
- Treatments per patient ranges from 1 to 4 with the average being ~1.5
- Hattiesburg is performing one treatment per patient unless the treatment is significantly shortened by filter clotting in which case they perform a second.
- Eisenhower Army Medical Center routinely performs 4 treatments on all patients
- Dr. Mink Chawla suggested scheduling 4 treatments with the idea of reassessing the need for continued treatments after the first 2 consecutive day treatments.
- My plan would be to limit treatments to 1 per patient with consideration for a second treatment if after the first treatment there was substantial clinical improvement followed by a redeterioration within 1 to 4 days. Reasoning for less treatments:
- This is a resource intensive treatment
- Spreading these resources out to more patients may better help us define who benefits from it and also reach more patients
- Treatment is not without risk
- More is not always better
- if the first treatment clears 99% of the pathogen is it worth going after the remaining 1% the next day?
- One could argue that the intracellular virus not cleared by the Seraph may cause recurrent viremia however waiting a few days to see signs of this seems reasonable in light of the resource intensive nature of the therapy and the lack of evidence that this is occurring. Furthermore if this is occurring whose to say waiting another 24 hours for the viremia build up is not the appropriate approach especially if your resources are limited. If a pt had access to 2 filters it may be better to use these filters in an every other day manner as opposed to a daily manner.
- Theoretically the Seraph knocks down the virus allowing the patients innate immune system to fight off the remaining virus and recover.
- This is an experimental therapy. There is no hard evidence that one Seraph treatment makes a difference in outcomes much less 4 treatments.
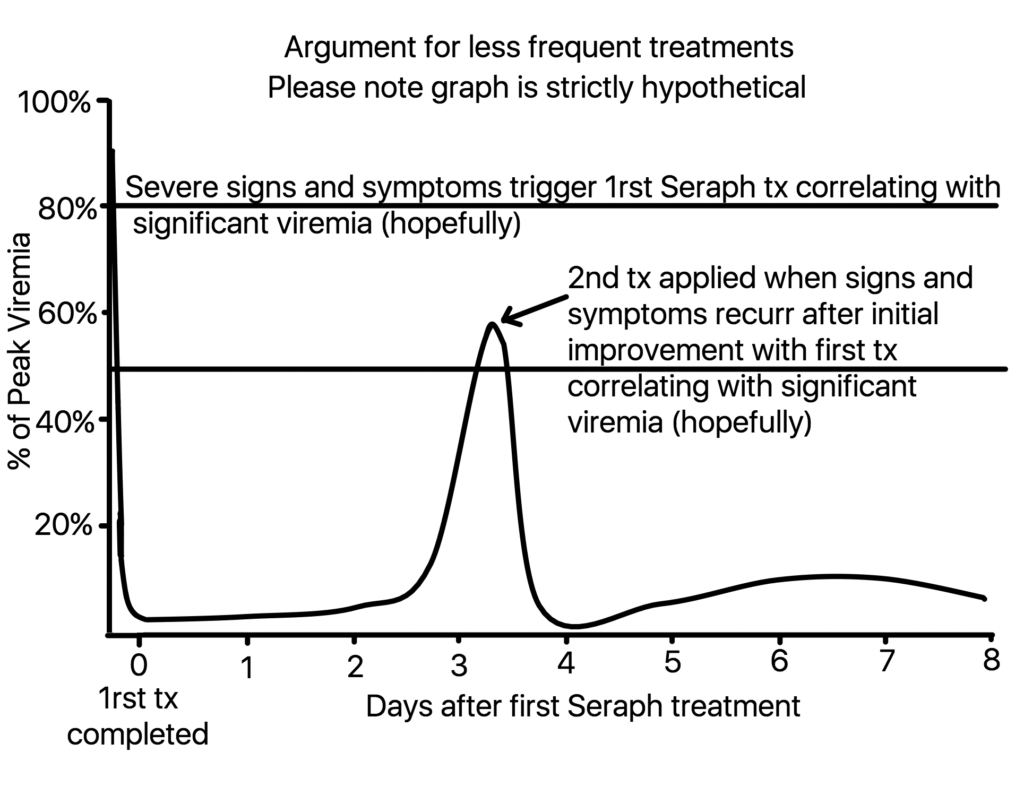
Had Seraphs been applied at day 1 or 2 after the first treatment in the hypothetical they would have been wasted assuming their benefit is largely due to removing the Covid virus.
is dependent on the blood flow rate achieved on the filter, most users are recommending filtration of 100 to 120 liters of blood per treatment session.
Dr. Olson on treatment lengthTo optimize sufficient exposure of patient’s blood to the Seraph 100 adsorption media, ExThera Medical recommends blood flow rates according to treatment duration as listed below:
| Blood Flow Rate | Number of Hours |
| 400 ml/min | 4 hours |
| 350 ml/min | 5 hours |
| 300 ml/min | 6 hours |
| 250 ml/min | 7 hours |
| 200 ml/min | 8 hours to <24 hours |
My opinion: Increasing BFR maximally as tolerated may enhance pathogen removal while limiting resource requirement. I would not however decrease the time of therapy to less than 4 hours even if a BFR of 500 mL/min is achieved. Reasoning:
- Duration of the blood during a pass through the filter may be as or more important for optimal virus binding/removal as the frequency of blood cell passes through the filter.
Heparinization during treatment
Dr. Olson on heparinization- Hattiesburg recommends rinsing the filters (Seraph & HD filter) and lines with 10,000 units of heparin prior to treatment initiation.
- Dr. Stephen Olson recommends a 500 unit heparin bolus at the start of treatment followed by a 300 unit continuous infusion during subsequent hours however this is when running without an HD filter in series.
- My plan if Heparin can be used:
- 5,000 unit heparin rinse of the Seraph, HD filter and lines pre-treatment
- 1,000 units at the start of treatment followed by 500 units every hour while on treatment
- Ptt check at 4 hours into treatment if session length to be 6 to 8 hours (Ptt goal 60-80)
- My plan if Heparin can not be used:
- 10,000 unit heparin pre-treatment followed by a 50 cc flush of both filters every hour while on treatment regardless of whether there are signs of clotting.
Potential benefits of the Seraph 100 Microbind Affinity Blood Filter device include:
- Removal of pathogens from the bloodstream
- Removal of inflammatory mediators from the bloodstream
Potential risks of the Seraph 100 Microbind Affinity Blood Filter device include:
- Hemodynamic compromise (e.g., hypotension, increased vasopressor requirement, reduced cardiac perfusion)
- Arrhythmia
- Blood loss
- Headache
- Nausea
- Cramping
- Hypertension
- Thrombosis
- Air embolism
- Infection
- Temperature dysregulation
- Allergic reaction
- Hemolysis
- Imbalance of certain chemicals (e.g., potassium, calcium, phosphate) in the blood •
- Acid-base abnormalities
- Thrombocytopenia / leukopenia
- Removal of other substances from the blood (e.g., vitamins, proteins, medications)
- Risks related to vascular access placement (e.g., infection, blood loss, thrombosis, tissue/organ injury)
- Risks related to anticoagulation (e.g., blood loss, allergic reaction)
- Itching
- Anxiety
- Convulsions/seizure
- Altered mental status
- Hemorrhage
- Clotting
- Pyrogenic reactions
- Cardiac dysrhythmia
- Chest pain
- Dyspnea
The following device settings have been validated for operation of the Seraph 100 Microbind Affinity Blood Filter device:
| Blood Priming Volume | 160 mL |
| Maximum Blood Flow Rate | 350 mL/min |
| Minimum Blood Flow Rate | 100 mL/min |
| Maximum Pressure Limit | 1,138 mmHg |
| Priming Fluid | Physiologic Saline |
Machine setup for running the Seraph
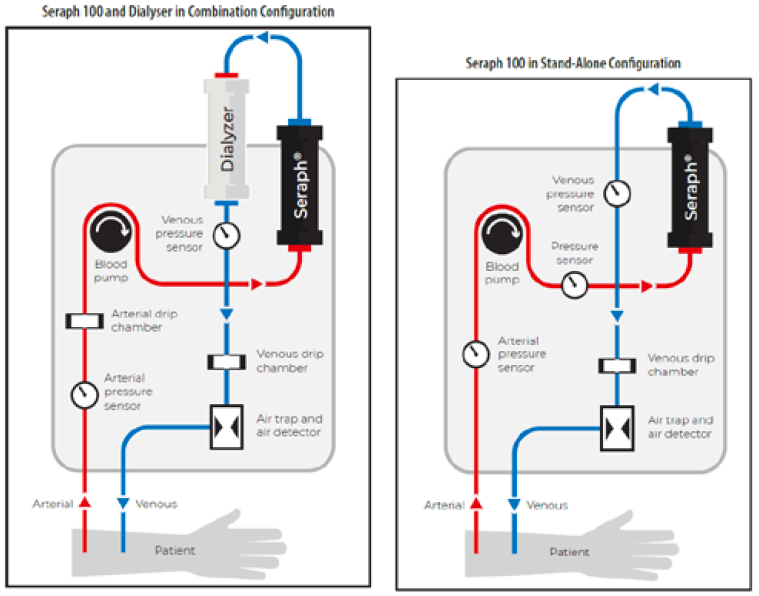
The Seraph 100 can be setup with the HD filter (dialyzer) in or out of the circuit.
The list below is a suggestion for programs with limited resources for applying the Seraph. It ranks patients based on their likelihood to respond to the Seraph.
Patients being offered their first treatment should have signs and symptoms that intubation is imminent in the next 24 to 48 hours or be on the ventilator.
A few comments on the rankings:
- non intubated is ranked above intubated due to possibly sparing them intubation if they respond to treatment and
- intubated takes some of the urgency off of their treatment and
- not intubated may be earlier in their disease hence more responsive to Seraph
- Retreatment with prior improvement inside of 21 days of their diagnosis are ranked ahead of patients being considered for their first treatment who are outside of 21 days since the further one is out from their diagnosis the less likely they are to respond.
- 1rst treatment candidates who are inside of 21 days of their diagnosis are ranked ahead of retreatment with prior improvement inside of 21 days in the interest of trying to help as many people as possible.
- ditto above for 1rst treatment candidates >21 to </= 28 days out from diagnosis being ranked ahead of retreatments >21 to </=28 days
- Retreatment without prior response are ranked near the bottom as their lack of response would seem to indicate low viremia.
| Ideal candidates |
|
| intubation appears imminent in the next 24 to 48 hours |
|
| Days from Covid positive test | rank |
| <1 day | 1 |
| 1 | 2 |
| 2 | 3 |
| 3 | 4 |
| 4 | 5 |
| 5 | 6 |
| 6 | 7 |
|
|
|
| Very good candidates |
|
| intubated |
|
| Days from Covid positive test |
|
| <1 day | 8 |
| 1 | 9 |
| 2 | 10 |
| 3 | 11 |
| 4 | 12 |
| 5 | 13 |
| 6 | 14 |
|
|
|
| Good candidates |
|
| intubation appears imminent in the next 24 to 48 hours |
|
| Days from Covid positive test |
|
| 7 | 15 |
| 8 | 16 |
| 9 | 17 |
| 10 | 18 |
| 11 | 19 |
| 12 | 20 |
| 13 | 21 |
|
|
|
| Medium Good candidates |
|
| intubated |
|
| Days from Covid positive test |
|
| 7 | 22 |
| 8 | 23 |
| 9 | 24 |
| 10 | 25 |
| 11 | 26 |
| 12 | 27 |
| 13 | 28 |
|
|
|
| Medium candidates |
|
| intubation appears imminent in the next 24 to 48 hours |
|
| Days from Covid positive test |
|
| 14 | 29 |
| 15 | 30 |
| 16 | 31 |
| 17 | 32 |
| 18 | 33 |
| 19 | 34 |
| 20 | 35 |
|
|
|
| intubated |
|
| Days from Covid positive test |
|
| 14 | 36 |
| 15 | 37 |
| 16 | 38 |
| 17 | 39 |
| 18 | 40 |
| 19 | 41 |
| 20 | 42 |
|
|
|
| Low priority candidates |
|
| Retreatment candidates with modicum of improvement reflected in respiratory parameters (PaO2, PaCO2, O2 sat, FiO2), blood pressure or Temp. curve during or within 24 hrs of latest Seraph |
|
| 2nd treatment (prior improvement) |
|
| Days from Covid positive test |
|
| 1 | 43 |
| 2 | 44 |
| 3 | 45 |
| 4 | 46 |
| 5 | 47 |
| 6 | 48 |
| 7 | 49 |
| 8 | 50 |
| 9 | 51 |
| 10 | 52 |
| 11 | 53 |
| 12 | 54 |
| 13 | 55 |
| 14 | 56 |
| 15 | 57 |
| 16 | 58 |
| 17 | 59 |
| 18 | 60 |
| 19 | 61 |
| 20 | 62 |
|
|
|
| 3rd treatment (prior improvement) |
|
| Days from Covid positive test |
|
| 2 | 63 |
| 3 | 64 |
| 4 | 65 |
| 5 | 66 |
| 6 | 67 |
| 7 | 68 |
| 8 | 69 |
| 9 | 70 |
| 10 | 71 |
| 11 | 72 |
| 12 | 73 |
| 13 | 74 |
| 14 | 75 |
| 15 | 76 |
| 16 | 77 |
| 17 | 78 |
| 18 | 79 |
| 19 | 80 |
| 20 | 81 |
|
|
|
| 4th treatment (prior improvement) |
|
| Days from Covid positive test |
|
| 3 | 82 |
| 4 | 83 |
| 5 | 84 |
| 6 | 85 |
| 7 | 86 |
| 8 | 87 |
| 9 | 88 |
| 10 | 89 |
| 11 | 90 |
| 12 | 91 |
| 13 | 92 |
| 14 | 93 |
| 15 | 94 |
| 16 | 95 |
| 17 | 96 |
| 18 | 97 |
| 19 | 98 |
| 20 | 99 |
|
|
|
| intubation appears imminent in the next 24 to 48 hours |
|
| Days from Covid positive test |
|
| 21 | 100 |
| 22 | 101 |
| 23 | 102 |
| 24 | 103 |
| 25 | 104 |
| 26 | 105 |
| 27 | 106 |
|
|
|
| intubated |
|
| Days from Covid positive test |
|
| 21 | 107 |
| 22 | 108 |
| 23 | 109 |
| 24 | 110 |
| 25 | 111 |
| 26 | 112 |
| 27 | 113 |
|
|
|
| Lower priority candidates |
|
| Retreatment candidates with modicum of improvement reflected in respiratory parameters (PaO2, PaCO2, O2 sat, FiO2), blood pressure or Temp. curve during or within 24 hrs of latest Seraph |
|
| 2nd treatment (prior improvement) |
|
| Days from Covid positive test |
|
| 21 | 114 |
| 22 | 115 |
| 23 | 116 |
| 24 | 117 |
| 25 | 118 |
| 26 | 119 |
| 27 | 120 |
|
|
|
| 3rd treatment (prior improvement) |
|
| Days from Covid positive test |
|
| 21 | 121 |
| 22 | 122 |
| 23 | 123 |
| 24 | 124 |
| 25 | 125 |
| 26 | 126 |
| 27 | 127 |
|
|
|
| 4th treatment (prior improvement) |
|
| Days from Covid positive test |
|
| 21 | 128 |
| 22 | 129 |
| 23 | 130 |
| 24 | 131 |
| 25 | 132 |
| 26 | 133 |
| 27 | 134 |
|
|
|
| Lowest priority candidates |
|
| Retreatment candidates without improvement during or within 24 hrs after latest Seraph |
|
| 2nd treatment (no prior improvement) |
|
| Days from Covid positive test |
|
| 1 | 135 |
| 2 | 136 |
| 3 | 137 |
| 4 | 138 |
| 5 | 139 |
| 6 | 140 |
| 7 | 141 |
| 8 | 142 |
| 9 | 143 |
| 10 | 144 |
| 11 | 145 |
| 12 | 146 |
| 13 | 147 |
| 14 | 148 |
| 15 | 149 |
| 16 | 150 |
| 17 | 151 |
| 18 | 152 |
| 19 | 153 |
| 20 | 154 |
| 21 | 155 |
| 22 | 156 |
| 23 | 157 |
| 24 | 158 |
| 25 | 159 |
| 26 | 160 |
| 27 | 161 |
|
|
|
| 3rd treatment (no prior improvement) |
|
| Days from Covid positive test |
|
| 2 | 162 |
| 3 | 163 |
| 4 | 164 |
| 5 | 165 |
| 6 | 166 |
| 7 | 167 |
| 8 | 168 |
| 9 | 169 |
| 10 | 170 |
| 11 | 171 |
| 12 | 172 |
| 13 | 173 |
| 14 | 174 |
| 15 | 175 |
| 16 | 176 |
| 17 | 177 |
| 18 | 178 |
| 19 | 179 |
| 20 | 180 |
| 21 | 181 |
| 22 | 182 |
| 23 | 183 |
| 24 | 184 |
| 25 | 185 |
| 26 | 186 |
| 27 | 187 |
|
|
|
| 4th treatment (no prior improvement) |
|
| Days from Covid positive test |
|
| 3 | 188 |
| 4 | 189 |
| 5 | 190 |
| 6 | 191 |
| 7 | 192 |
| 8 | 193 |
| 9 | 194 |
| 10 | 195 |
| 11 | 196 |
| 12 | 197 |
| 13 | 198 |
| 14 | 199 |
| 15 | 200 |
| 16 | 201 |
| 17 | 202 |
| 18 | 203 |
| 19 | 204 |
| 20 | 205 |
| 21 | 206 |
| 22 | 207 |
| 23 | 208 |
| 24 | 209 |
| 25 | 210 |
| 26 | 211 |
| 27 | 212 |
|
|
|
| intubation appears imminent in the next 24 to 48 hours |
|
| Days from Covid positive test |
|
| >28 or more days | 213 |
| |
|
| not intubated | |
| Days from Covid positive test | |
| >28 or more days | 214 |
| Tiebreakers |
|
| Fi02 higher wins |
|
| pressors y/n: yes wins |
|
| Temp >100.4 in past 24 Hrs y/n: yes wins |
|
| Age: younger wins |
|
| # of comorbidities (DM, HTN, BMI >/= 30, cigarette use): less wins |
|
| flip a coin |
|
FDA Fact Sheet for Healthcare Providers Seraph Use
FDA Fact Sheet for Patients about Seraph Treatment
Rankings and Tx time calculator Excel spreadsheet download
Weekly listing sheet for Seraph treatment Excel spreadsheet download
Updated 10/10/20